

Heart attack in young adults can happen, but age alone cannot tell you your personal risk. Your health history, family history, and other risk factors can help show what deserves attention. For women, reproductive history may add useful context, even years after pregnancy.
A heart attack in a younger person can feel unexpected, especially when they seem healthy. Yet a single risk factor does not predict what will happen to you. Your blood pressure, cholesterol, diabetes history, and family background all contribute to a fuller picture.
Reproductive events, including pregnancy complications and early menopause, can also be relevant to a woman’s long-term heart health. Their importance depends on the rest of her medical history, not on any one event alone. A clinician can consider your history as a whole rather than treating any one risk marker as a prediction.
Key Takeaways
- Heart attacks can affect younger adults.
- Age alone does not define personal risk.
- Family and medical history add useful context.
- Reproductive history can inform women’s prevention discussions.
- A risk marker is not an individual prediction.
Heart Attack in Young Adults: What Studies Show About Rising Rates
About one in five heart attacks occur in people under 40, even though age alone cannot explain the trend. Yes, studies show a concerning pattern among younger adults, but heart attack rates and death rates measure different things. Among people under 40, the heart attack rate grew by nearly 2% each year from 2000 to 2016.
That figure describes the rate of heart attacks, not the number of deaths. From 2010 to 2019, U.S. heart-disease death rates fell 5.5%; in 2020, they rose 4.1%. Among adults ages 35-54, the death rate rose 12% in 2020, representing about 10 years of lost progress among younger adults.

Mortality research measures deaths, not every heart attack. Among adults ages 25-44, mortality from myocardial infarction and heart failure combined increased after 2010. A CDC WONDER mortality study found that overall age-adjusted acute myocardial infarction mortality rose in 2020 and 2021, after declining through 2019.
Heart attack rates count events; mortality rates count deaths, and the two measures answer different questions.
In 2022, growing evidence suggested COVID-19 may be associated with new or worsening cardiovascular disease. More investigation was needed, and the 2020 increase in heart-disease deaths does not prove that COVID-19 caused more heart attacks.
Rates and mortality can move differently, so population trends do not tell you why one person had an event. Treat a change in death rates as a warning about population health, not proof of what caused an individual heart attack.
Which Risk Factors and Tests Matter Most in Your 20s and 30s?
Your personal risk depends on more than your age, and a blood pressure check, cholesterol test, and family history are practical places to start. Those basics matter because risk factors can develop long before symptoms appear. For adults in their 20s, clinicians assess the individual risk factors directly; the PREVENT-ASCVD equations start at age 30.
PREVENT-ASCVD equations are risk equations that estimate 10-year and 30-year cardiovascular disease, ASCVD, and heart failure risk in adults ages 30-79 without known cardiovascular disease. They are recommended for primary prevention in adults ages 30-79 without known ASCVD or subclinical atherosclerosis and with LDL-C of 70-189 mg/dL. They do not provide a personal estimate for someone in their 20s.
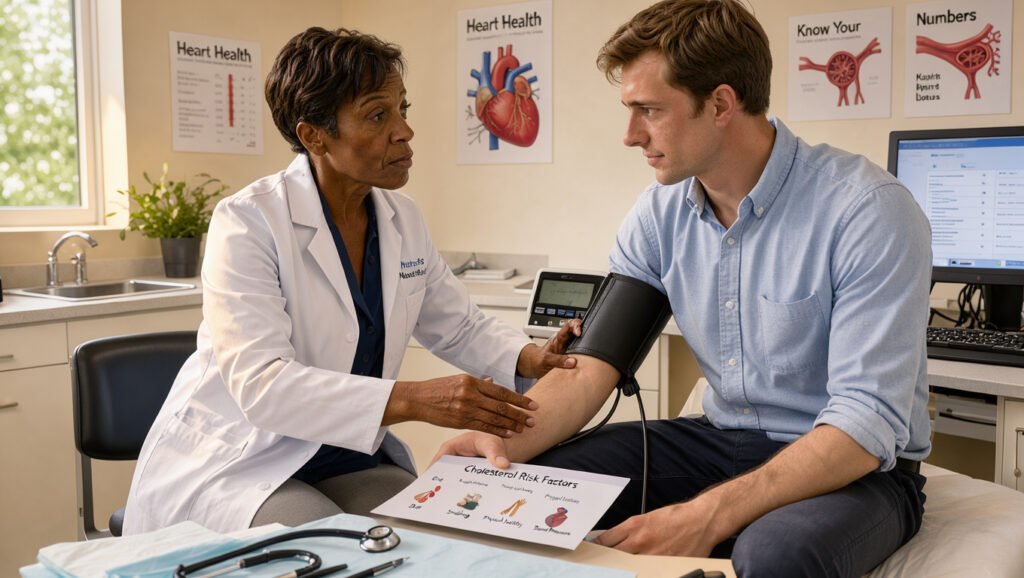
Blood Pressure, Diabetes, and Family History
High blood pressure, diabetes, obesity, and family history can shape risk at a young age. A study of 13,000 young adults found diabetes prevalence rose from 3% in 2009 to 4.1% in 2020. Obesity rose from 32.7% to 40.9% over the same period. Reported hypertension incidence increased from 9% in 2009-2010 to 12% in 2011-2022.
Increased-risk adults can begin blood pressure and cholesterol screening at age 20. Under the 2017 ACC/AHA guideline criteria, hypertension affects 1 in 2 U.S. adults. By a different measure, age-standardised hypertension prevalence was 34.5% in 2009-2010 and 34.3% in 2021-2023, with no overall change reported. These figures use different measures and periods, so they are not contradictory. Hypertension was a primary or contributing cause of approximately 664,000 U.S. deaths in 2023, and hypertension-related cardiovascular death rates have nearly doubled over two decades.
Discuss these five clues with a clinician:
- High blood pressure
- Diabetes
- LDL-C of at least 160 mg/dL in a young adult
- A strong family history of premature ASCVD
- High triglycerides or cardiovascular-kidney-metabolic syndrome
Cholesterol Tests and PREVENT-ASCVD Estimates
About 1 in 4 U.S. adults has high LDL cholesterol. A 10-year ASCVD estimate is low below 3%, borderline from 3% to less than 5%, intermediate from 5% to less than 10%, and high at 10% or more. At borderline risk, LDL-lowering medication can be considered; at intermediate risk, it should be considered after a clinician-patient discussion.
LDL-C goals are below 100 mg/dL for primary prevention at borderline or intermediate risk, below 70 mg/dL for high-risk primary prevention, and below 55 mg/dL for secondary prevention in people with ASCVD at very high risk. Earlier lipid-lowering medication may be considered for young adults with LDL-C of at least 160 mg/dL or a strong family history of premature ASCVD. The American College of Cardiology’s CVD Risk Estimator Plus describes the PREVENT equations, developed using data from more than 6 million people. Its optional HbA1c predictor issue was corrected on October 14, 2026.
| Test or tool | Who or when it applies | Key number or criterion | What it helps assess |
|---|---|---|---|
| PREVENT-ASCVD | Adults ages 30-79 without known ASCVD or subclinical atherosclerosis; LDL-C 70-189 mg/dL | 10-year and 30-year estimates | Cardiovascular disease, ASCVD, and heart failure risk |
| Lp(a) | Measure at least once in adulthood | 125 nmol/L or 50 mg/dL; 250 nmol/L | Long-term heart attack or stroke risk; first level is about 1.4-fold higher, second at least two-fold higher |
| Selective CAC scan | Men age 40 or older, and women age 45 or older with borderline or intermediate risk | Selective use | Guides statin decisions |
| Apolipoprotein B | Cardiovascular-kidney-metabolic syndrome, Type 2 diabetes, high triglycerides, or known cardiovascular disease | Consider after LDL-C and non-HDL-C goals are reached | Residual risk |
Myocarditis Is Different From a Heart Attack
Heart disease is a broad category, not another name for a heart attack. Myocarditis is inflammation of the heart muscle, while a heart attack involves a blocked blood supply to heart muscle. A risk assessment helps guide prevention; it is not itself a diagnosis.
If you are younger than 30, ask a clinician to assess your risk factors directly rather than applying PREVENT outside its age range.
How Does Reproductive History Shape Women’s Heart Disease Risk?
A history of gestational diabetes, preeclampsia, or early menopause can matter to a woman’s cardiovascular risk assessment years later. These details stay relevant even when the pregnancy or menopause transition is long past. The 2026 ACC/AHA dyslipidemia guideline identifies all three as reproductive risk markers for cardiovascular disease.
Reproductive history adds context to risk assessment, but it does not prove cause or predict an individual outcome. A clinician can consider it alongside blood pressure, cholesterol, diabetes, family history, and other health details.

Pregnancy Complications as Cardiovascular Risk Markers
Gestational diabetes and preeclampsia are important to mention at preventive care visits. Mothers with prior gestational diabetes had approximately 40% higher risk of cardiovascular outcomes such as heart attack and stroke than mothers without it.
That association describes a difference between groups, not a personal forecast. It also does not establish that gestational diabetes caused a later heart attack or stroke. A pregnancy complication can be a useful clue when you and your clinician review your health over time.
Early Menopause and Long-Term Risk
Early menopause is another reproductive risk marker recognised in the 2026 guideline. Mentioning when menopause began can help complete the risk picture, especially when other risk factors are present. You do not need to wait for a heart problem before sharing this part of your medical history.
Include pregnancy complications and menopause timing in the history shared at a preventive-care appointment.
What Are the Warning Signs of a Heart Attack, and When Is It an Emergency?
A heart attack can cause chest discomfort, shortness of breath, or symptoms that are easy to mistake for something less serious. Symptoms can vary, and they may not begin with obvious chest pain. Chest discomfort remains the most common symptom for women and men.
It may feel like pressure, squeezing, fullness, or pain in the centre of the chest. The feeling can last more than a few minutes or go away and return. A heart attack occurs about every 40 seconds in the United States.

Chest Discomfort and Breathing Changes
Possible heart attack symptoms include:
- Chest pressure or discomfort
- Shortness of breath
- Discomfort in the arm, back, neck, jaw, or stomach
- Cold sweats, nausea, or lightheadedness
- Unusual tiredness or weakness
These signs can appear together or separately. Younger adults may dismiss them as stress, indigestion, or fatigue, but age does not rule out an emergency. A sudden change from your usual health deserves attention, particularly when symptoms feel severe or keep returning.
Symptoms Beyond the Chest in Women
Women may have symptoms beyond chest discomfort, though chest discomfort is still the most common symptom for women and men. Nausea, stomach discomfort, or unusual fatigue may be easier to dismiss as a routine illness or a busy day.
Do not wait for every possible sign to appear before acting. The American Heart Association advises calling 911 immediately for signs of a heart attack. Emergency responders can begin care on the way to the hospital, which is why driving yourself is not the safer choice.
Call 911 immediately for possible heart attack symptoms instead of driving yourself or waiting to see if they pass.
How Can Younger Adults Lower Risk and Support Recovery?
Prevention is built from repeatable habits, while recovery after a heart attack can include both cardiac rehabilitation and emotional support. Small choices add up when practised over time. Health-behaviour counselling should start in youth to support healthy habits and reduce lifelong exposure to atherogenic lipoproteins.
Life’s Essential 8 groups heart-health measures into five practical areas:
- Nutritious eating and regular activity
- Tobacco avoidance and healthy sleep
- Weight management
- Cholesterol and blood sugar
- Blood pressure

Daily Habits That Support Heart Health
The American Heart Association recommends at least 150 minutes of moderate-intensity aerobic activity each week, or 75 minutes of vigorous activity, or a combination. Muscle-strengthening activity at moderate to high intensity is recommended at least twice weekly.
| Activity | Intensity | Weekly target |
|---|---|---|
| Aerobic activity | Moderate intensity | At least 150 minutes |
| Aerobic activity | Vigorous intensity | At least 75 minutes |
| Muscle-strengthening activity | Moderate to high intensity | At least twice weekly |
Recovery Includes Cardiac Rehabilitation
Cardiac rehabilitation can support physical recovery after a heart attack. Emotional health also deserves attention: an estimated 33%-50% of survivors may experience psychological distress. Persistent distress lasting up to 12 months is associated with nearly 1.5 times the likelihood of a future cardiac event, though more research is needed to establish cause and effect.
Emotional distress after a heart attack deserves care, even though an association with future events does not prove that distress causes them.
An estimated 1 in 3 heart attack survivors develops depression annually, compared with 8.4% of U.S. adults in the general population. Anxiety and stress may affect up to 50% of survivors during hospitalisation and persist in 20%-30% for several months or longer. Post-heart-attack anxiety is associated with 1.3 times the likelihood of another heart attack or death; depression and PTSD are each associated with twice the risk of recurrent cardiovascular events or mortality.
Evidence-based options include cognitive behavioural therapy, medication, mindfulness-based stress reduction, regular exercise, and improved sleep. Selective serotonin reuptake inhibitors are considered safe and effective for depression in people with cardiovascular disease.
Heart Failure in Your 20s and Long-Term Outlook
Heart failure life expectancy in your 20s cannot be estimated from age alone. Cause, heart function, other health conditions, and treatment affect outlook, so an individualised discussion with a clinician is needed. The diagnosis does not by itself determine how long you will live.
Ask your care team to include emotional health and rehabilitation goals in the recovery plan, as well as physical ones.
Conclusion
You do not have to wait for symptoms to take your heart health seriously. Being young does not rule out cardiovascular risk, and family history can help you and your clinician understand what deserves attention.
For women, reproductive history can add useful context to prevention, even years after pregnancy or menopause. A risk marker is not a prediction, but sharing it can help make a preventive-care discussion more complete.
Schedule a preventive-care appointment to discuss blood pressure, cholesterol, family history, and pregnancy history. Bring your blood pressure and cholesterol questions, family history, and reproductive history to your next appointment.